Beginner’s Guide to Peptide Therapy
We explore the world of therapeutic peptides to help you understand what they are, what they do, and much more.
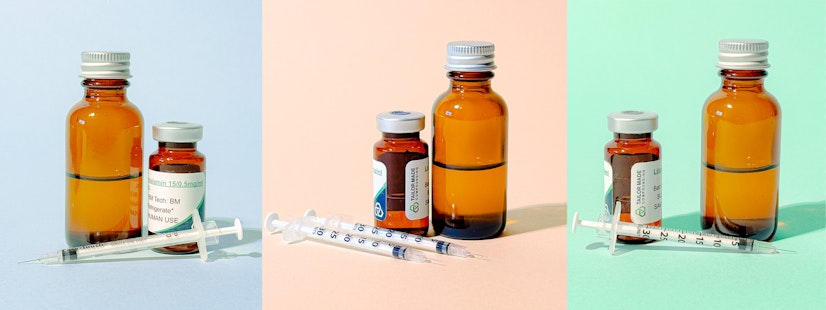
Photo by Innerbody Research
In recent years, the peptide space has seen a significant uptick in drug discovery, clinical research, and therapeutic applications.25 Even so, these treatments remain unfamiliar to many prospective patients, who aren’t exactly sure what peptides are or how they work.
It’s not their fault. Peptides are a complex subject with strange drug names, shared and sometimes contradictory potential effects, and confusing regulatory statuses. That’s why we’ve written this guide and structured it as we have. Where applicable, as we discuss each aspect of different peptide therapies, we start with a high-altitude view and then zoom in on the caveats and exceptions that make them unique. That way, you get both a broad sense of how peptides can work and a specific sense of which ones might work for you.
In the end, we trust you’ll have all the information you need to make the best-informed decision about your own peptide therapy, should you pursue it. And if you do decide to look for a reputable online source, we’d recommend a telehealth platform called UVG Health.

UVG Health is a LegitScript-certified telehealth platform that partners with licensed independent medical practitioners and state-licensed 503A compounding pharmacies.
Working with licensed providers, UVG offers a pathway to pharmaceutical-grade peptides delivered to your doorstep. Its patient support infrastructure also includes free educational resources, such as a discovery call with a specialist who guides interested health consumers to treatments that align with their health goals. Book a free discovery call online to explore peptide therapies that may be suitable for you.
Jump to:
Why you should trust us
Over the past two decades, Innerbody Research has helped tens of millions of readers make more informed decisions about staying healthy and living healthier lifestyles.
Our team has been exploring the peptide space for years. For every hour we’ve put into writing about peptides, we’ve devoted two or three hours to research. All told, our total clock time on the subject exceeds 1,000 hours. Along the way, we’ve gained invaluable insights from medical providers who prescribe peptides, as well as from people who use them.
Additionally, like all health-related content on this website, this guide was thoroughly vetted by one or more members of our Medical Review Board for accuracy and will continue to be monitored for updates by our editorial team.
What exactly are peptides?
Peptides occur naturally in the body (endogenous) but can also be administered externally (exogenous).
The basics that underlie all peptides, endogenous and exogenous alike, are these:
- Peptides are strings of amino acids.
- Amino acids are molecules that combine to form protein molecules.
- Proteins are essential for a diverse array of bodily functions, including but not limited to immune function, muscle contraction, metabolism, physical growth, physical structure, blood oxygenation, and sexual arousal.1
The human body needs an adequate supply of 20 amino acids to function properly,2 but those 20 amino acids can combine in thousands of unique sequences to form different peptides with distinct biological functions. By supplementing your endogenous supply of peptides with exogenous sources, you may provide your body with more of the resources it needs to carry out specific functions.
Therapeutic peptides
Those exogenous sources, when used to treat health conditions, are called therapeutic peptides. Given the varied roles that peptides assume in the human body, you can imagine that therapeutic peptides have a vast array of potential applications in human health. By way of example, consider this table of common therapeutic peptides and their primary intended health outcomes:
In many cases, therapeutic peptide prescriptions are given off-label (i.e., to treat health conditions other than what a peptide may be approved for).
Take tesamorelin, for example. As an analog of endogenous growth hormone-releasing hormone (GHRH), tesamorelin boasts a metabolism-stimulating activity that has led to its being approved as a treatment for lipodystrophy, or abnormal adipose fat accumulation associated with antiretroviral therapy for HIV.3 But this same activity can help non-HIV individuals shed abdominal fat of their own, while the peptide’s GHRH properties make it a suitable therapy for people looking to increase their lean mass. Therefore, tesamorelin is sometimes given as an off-label prescription for weight loss or muscle growth.
Routes of administration
With regard to routes of administration, therapeutic peptides are often injectables, administered subcutaneously by needle. That’s because peptides degrade easily in the digestive tract and tend to be too large molecularly to permeate the skin or intestinal lining,5 often yielding a bioavailability as low as 1-2%.6
Insider Tip: Peptide needles are typically quite thin and so cause much less discomfort than a shot at the doctor’s office.
But there are some peptides that have a small enough molecular size that they easily transfer into the bloodstream as either an oral or a topical supplement. A couple of good examples are collagen, with an oral bioavailability as high as 63%,7 and GHK-Cu (copper peptides), which can pass through the skin in therapeutically effective amounts, per a 2010 study.8
Preparation and storage of injectable peptides
Nowadays, injectable peptides often come premixed, ready to use, whereas in years past they normally came in powder form needing reconstitution. Still, it’s helpful to know how to reconstitute a peptide powder, should you need to.
The reconstitution process entails drawing a measure of bacteriostatic water into a syringe and then introducing that water to the peptide powder. Your prescriber’s instructions should specify how much water to use and how to dissolve the powder. However much water you’re supposed to use, avoid shaking the solution, as it can degrade the peptide.
Whether reconstituted or premixed, a peptide should last at least a month when stored appropriately. The ideal storage temperature is around 4°C, or 39°F,9 so a refrigerator is the best place for it.
Major peptide types and their benefits
While peptides can potentially serve myriad health goals, we can broadly organize the most commonly sought-after peptides into five categories based on their primary benefits. In the following sections, we discuss those categories and the peptides most often associated with them.
Weight loss peptides (GLP-1 RAs)
Originally developed as diabetes treatments, glucagon-like peptide 1 receptor agonists (GLP-1 RAs) exhibit mechanisms of action on metabolism and the pancreas that promote weight loss by:26
- Slowing digestion: A longer time to gastric emptying correlates not only with a decreased appetite but also with a milder glucose spike.27 28 A decreased appetite means less desire to consume excess calories, and a less severe spike indicates tighter regulation over a significant weight-gain factor.29
- Increasing feelings of fullness: When you do get hungry, a GLP-1 RA can help you reach satiety sooner than you normally would. Ideally, that leads to eating less food during mealtimes and, therefore, consuming fewer calories throughout the day.
Today, the most popular and widely used peptides for weight loss are tirzepatide and semaglutide, which you may know by the respective brand names Mounjaro and Ozempic. Both have a wealth of scientific support for their efficacy, but tirzepatide has a bit more evidence behind it. In a 2021 study, for example, subjects who received tirzepatide lost around 4-12 more pounds than their semaglutide counterparts.30 But semaglutide is still a terrific option for fast weight loss, and it’s more easily accessible through reputable telehealth platforms.
Body recomposition
Body recomposition refers to the process of gaining muscle and shedding fat. In our categorization, it’s this muscle growth factor that separates body recomposition peptides from GLP-1 RAs.
Many body recomposition peptides are growth hormone secretagogues, or substances that stimulate the body’s production of growth hormone, which itself promotes physical growth and helps regulate body fat composition through a different hormone called insulin-like growth factor-1.31 32 Some of the more commonly used growth hormone secretagogue peptides are CJC-1295, ipamorelin, sermorelin, and tesamorelin. (Tesamorelin is also prescribed to treat HIV-associated lipodystrophy, or excess abdominal fat accumulation resulting from antiretroviral therapy. That is, in fact, the application for which it’s FDA-approved.)
Besides growth hormone secretagogues, there are several uncategorized peptides that many people use to increase their muscle mass. Examples of these include BPC-157 and TB4/TB500, which are often used together for their synergistic potential to stimulate muscle gain while speeding up recovery.
General wellness
Peptides for general wellness constitute the broadest category, as wellness refers to several target health outcomes: longevity, immune health, and quality of life (the last of these itself being a pretty broad designation). Examples of such peptides include:
- MOTS-c: MOTS-c is a naturally occurring protein hormone that may improve metabolic function,33 reduce inflammation,34 and improve bone health,35 among other things.
- Epitalon: Consisting of four amino acids, epitalon can help preserve the lengths of telomeres (the caps on the ends of chromosomes) and regulate melatonin. In doing so, it may stave off age-related diseases associated with telomere shortening,36 strengthen the immune system,37 and improve sleep health.38
- Delta sleep-inducing peptide (DSIP): As its name suggests, DSIP helps with sleep. It may also attenuate stress and have applications as an anticonvulsant, antidepressant, and neuroprotective agent.39
- Thymosin alpha-1: Thymosin alpha-1 may offer numerous benefits related to immune function, including but not limited to treating hepatitis B, treating infections, improving vaccine efficacy, and reducing the toxicity of chemotherapy.40
- GHK-Cu: GHK-Cu is a complex of copper and the peptide GHK. It has quality-of-life applications related to skin health, as research supports its ability to tighten loose skin, improve skin firmness, reduce photodamage, promote wound healing, and more.41
- Insulin: Insulin is a quality-of-life treatment for managing blood sugar. It’s helpful for people with type 2 diabetes and necessary for those with type 1 diabetes.42
Cognitive enhancement
Cognitive enhancement peptides are similar to nootropics in that they can improve focus, memory, and mental clarity, as well as associated factors like anxiety and mood. Two promising synthetic peptides in this category are Selank and Semax. Studies on the former have shown that it can produce a stable and sustained influence on learning and memory,43 while the latter may be able to support the differentiation, maturation, and survival of neurons in the brain.44
Another potential cognitive enhancement peptide is Pinealon, which can improve learning and memory by modulating gene expression and neurotransmitter activity. In rodents at least, Pinealon administration has correlated with an improved ability to negotiate a maze,45 suggesting that the subjects could acquire and retain information more effectively.
Sexual function
Peptides for sexual function are either alternatives or adjuncts to more ordinary prescription treatments such as sildenafil and tadalafil. One such peptide, called PT-141 (a.k.a. bremelanotide), has been described as a “promising way to treat [hypoactive sexual desire disorder],”46 a condition characterized by a chronic lack of sexual desire.47 PT-141 is available as a prescription for premenopausal women under the brand name Vyleesi, clinical trials for which have shown the drug to both improve sexual desire and decrease feelings of associated distress.48
PT-141 has also been tested in men, as in a 2005 study that coadministered the peptide with sildenafil to subjects with ED who either had not responded to or could not tolerate single-therapy treatment. Among this cohort, coadministration was deemed to be a “viable therapy.”49
Another possible sexual peptide solution, for both men and women, is oxytocin, which may have some role in stimulating sexual attraction.50 But more research is needed, as some studies have found oxytocin to be ineffective at improving sexual behavior.51
How therapeutic peptides are made
Besides their specific use applications, we can broadly classify therapeutic peptides into three categories based on how they’re produced for the market:
- Bioactive peptides
- Synthetic peptides
- Recombinant peptides
Their differences lie not in their respective efficacy but in their feasibility and cost-effectiveness. That is, from a production perspective, some peptide varieties lend themselves more to one production method than either of the other two.
Bioactive peptides
Bioactive substances are found in organic matter, such as plants, animals, and animal products, so bioactive peptides might also be categorized as natural peptides.10
Bioactive peptides can be consumed via dietary sources, including but not limited to eggs, soy, legumes, meat (including seafood), and dairy.11 Or else they can be isolated, extracted, and processed into oral or even topical supplements. Two common production techniques for bioactive peptides are enzymatic hydrolysis and microbial fermentation, which are both ways to break proteins down into smaller peptides or individual amino acids.12
The realm of bioactive peptides is somewhat limited because, remember, peptides can easily break down in the digestive tract, and many are too molecularly large to permeate the skin or intestinal lining.5 But there are several peptide varieties that are readily bioavailable by oral or transcutaneous administration, such as collagen and GHK-Cu.
Synthetic peptides
Synthetic peptides are lab-derived, created by deliberately linking amino acids in sequences that mimic endogenous peptides. It’s by this method that you get some of the best-known pharmaceutical peptides, like semaglutide, tirzepatide, and tesamorelin.
If endogenous peptides are like OEM parts in the machinery of your body, then we can liken synthetic peptides to 3D prints: in terms of structure and function, they’re similar if not identical.
The drawback of synthetic peptides is that they’re largely limited to short chains of up to 50 amino acids, as longer peptides present a greater challenge from a large-scale manufacturing perspective.13
Recombinant peptides
Recombinant peptides are those produced via recombinant DNA technology, by which scientists manipulate and isolate DNA segments to express the genes of specific peptides.14 Think of it as the Venn common ground between the bioactive and the synthetic, a biotechnological hybrid relying on both organic and laboratory processes. With recombinant technology, therapeutic peptide chains can more easily exceed 50 amino acids. Producing such peptides can be costlier up front, but may be more efficient on larger scales.
The safety of peptide therapy
Many therapeutic peptides are generally safe for nonpregnant, non-breastfeeding people with specific allergies, with adverse events being mostly limited to mild and transient flu-like effects and (for injectables) injection site reactions.
But sometimes there are higher risks, especially with regard to synthetic and recombinant peptide forms:
Immunogenicity
Most notably, per a 2020 assessment on therapeutic peptide safety, synthetic and recombinant peptides pose the risk of immunogenicity — the ability of a substance to provoke an immune response.15 An immunogenicity-inducing peptide, when introduced to the body, would cause the body’s immune system to perceive the peptide not as a medication but as a threat. At the very least, immunogenicity would trigger the production of antibodies that neutralize the peptide’s effects; at worst, the same antibodies can elicit life-threatening complications, possibly even systemic anaphylaxis.16 17
The FDA currently identifies several peptides that may pose a significant risk of immunogenicity: growth hormone releasing peptide-2, growth hormone releasing peptide-6, ipamorelin acetate, and kisspeptin-10.19 22
Carcinogenicity
Carcinogenicity is the ability of a substance to cause cancer. Some peptides, by virtue of their action, are potentially and incidentally carcinogenic. A good example of this is growth hormone secretagogues — peptides that facilitate growth hormone secretion — whose capacity to promote physical growth can trigger the growth and spread of tumors.18 For that reason, peptides such as sermorelin, tesamorelin, and CJC-1295 are contraindicated for people with active cancer, as well as those with a personal or familial history of cancer.
Current legal status of therapeutic peptides
Peptide legality is a complex issue. Some therapeutic peptides (e.g., collagen) are readily available over the counter. Some need a doctor’s prescription but are otherwise widely available (e.g., GLP-1 RAs like semaglutide and tirzepatide). But then there are others that, in the United States, currently drift in a state of legal limbo.
The complexities arise from Section 503A of the Federal Food, Drug, and Cosmetic Act, which relates to the necessary conditions for drug compounding.20 The rules state that the compounded drug must come from accredited compounding pharmacies, and that it must either:21
- Be compounded from an existing FDA-approved drug product, or components thereof
- Be compounded from substances with a USP monograph
- Use drug products included on the 503A bulks list (the FDA’s roster of compoundable substances)21
While implementing Section 503A, the FDA created three interim categories for nominated bulk drug substances awaiting evaluation. Several therapeutic peptides — including but not limited to BPC-157, CJC-1295, epitalon, and MOTs-c — have spent some time on the Category 2 list, indicating the potential for significant safety risks, but many of them have since been removed after their nominations were withdrawn. Removal doesn’t imply approval or resolution of safety concerns, however. It doesn’t mean prohibition, either.
Rather, Section 503A allows for exemptions as long as you have a valid prescription indicating that a compounded treatment is “necessary for the identified patient.”23 Many non-mainstream peptides are therefore accessible in a restricted fashion.
Also worth noting is that several peptides may be on their way toward wider availability. In July 2026, an FDA advisory panel voted to lift restrictions on BPC-157, TB-500, KPV, MOTS-c, epitalon, and Semax, and a handful of others (LL-37, GHK-Cu, Dihexa, Melanotan II, and PEG-MGF) will undergo a vote in February 2027.
The panel’s decision is only a recommendation, not an approval, but it may lead to further clinical studies that can help validate whether particular peptides are indeed safe and effective.
Safe retail sources for peptide prescriptions
Several well-known telehealth platforms sell pharmaceutical-grade peptides, but most catalogs are limited to GLP-1 RAs such as semaglutide and tirzepatide. Hims, Hers, Henry Meds, Ro, and Strut are some of the more popular outfits where you can find GLP-1 RAs online.
Lesser-known peptides are available online, too, but you need to be vigilant about where you shop. Some purveyors peddle research-grade products not intended for human consumption, and unless you only mean to conduct your own in vitro experiments, you should leave them alone. That’s because research-grade peptides aren’t subject to the same quality controls as their pharmaceutical-grade counterparts, and many have purity levels as low as 60%.4 Thus, they have a greater potential to be toxic and cause the life-threatening adverse effects we discuss under “Therapeutic peptide safety.”
For the pharmaceutical-grade stuff, you want to make sure your chosen platform is a legitimate operation. Here are a few green flags to watch for:
- LegitScript certification, a compliance designation that effectively denotes that an online business in a high-risk sector (e.g., telehealth) follows ethical practices and deals in legitimate products/services
- Medical oversight, which entails review by a licensed medical practitioner before your prescription is approved
- Partnership with legitimate human-use peptide sources, such as a state-licensed 503A compounding pharmacy
There are a handful of reputable telehealth platforms that offer non-mainstream peptides and check all three of the above boxes. The one we recommend is UVG Health, not only because of its treatment offerings but also for its commitment to educating health consumers about peptides. The service we most appreciate is its free discovery call, a conversation with a specialist who discusses peptides that may align with your health goals, breaks down their mechanisms and protocols, and walks you through UVG’s prescription process.
If you’re indicated for any treatments, your eligibility undergoes review by a licensed independent physician or nurse practitioner. Approved prescriptions are then sent to a state-licensed compounding pharmacy for fulfillment. From there, it ought to be just a matter of days before your medication arrives at your home. And in our experience, the cold-packed container should still be cold when it arrives, which is a major plus with regard to preserving the peptides’ integrity.
The future of peptide therapy
The 503A bulks list is a living document, continuously in flux. The restricted peptides we’ve named may one day find their way onto the list, thereafter becoming more widely available to prescribed patients.
Meanwhile, new potential peptide drugs are being discovered,24 suggesting promising but as-yet-undetermined directions in the treatment of common health concerns. So, as developments and trends emerge, we’ll update this guide accordingly, keeping you current on the information you need to direct your own peptide therapy.
Sources
Innerbody uses only high-quality sources, including peer-reviewed studies, to support the facts within our articles. Read our editorial process to learn more about how we fact-check and keep our content accurate, reliable, and trustworthy.
- Physiopedia. (n.d.). Proteins. Physiopedia.
- Lopez, M. J., & Mohiuddin, S. S. (2024). Biochemistry, essential amino acids. StatPearls [Internet].
- National Institute of Diabetes and Digestive and Kidney Diseases. (2018). Tesamorelin. LiverTox: Clinical and Research Information on Drug-Induced Liver Injury [Internet].
- De Groot, A. S., et al(2023). Immunogenicity risk assessment of synthetic peptide drugs and their impurities. Drug Discovery Today, 28(10), 103714.
- Brayden, D. (2020). Nanotechnology provides new methods for oral delivery of peptides. Research Outreach.
- Renukuntla, J., et al. (2013). Approaches for enhancing oral bioavailability of peptides and proteins. International Journal of Pharmaceutics, 447, 75-93.
- Wang, L., et al. (2015). Bioavailability and bioavailable forms of collagen after oral administration to rats. Journal of Agricultural and Food Chemistry, 63(14), 3752-3756.
- Hostynek, J. J., Dreher, F., & Maibach, H. I. (2010). Human skin penetration of a copper tripeptide in vitro as a function of skin layer. Inflammation Research, 60(1), 79-86.
- National Institute for Biological Standards and Control. (n.d.). Peptide handling, dissolution & storage. NIBSC.
- Lee, B., & Kim, C. Y. (2022). Dietary bioactive compounds and health. Foods, 11(16), 2395.
- Chakrabarti, S., Guha, S., & Majumder, K. (2018). Food-derived bioactive peptides in human health: Challenges and opportunities. Nutrients, 10(11), 1738.
- Akbarian, M., et al. (2022). Bioactive peptides: Synthesis, sources, applications, and proposed mechanisms of action. International Journal of Molecular Sciences, 23(3), 1445.
- Wang, L., et al. (2022). Therapeutic peptides: Current applications and future directions. Signal Transduction and Targeted Therapy, 7(1), 1-27.
- National Human Genome Research Institute. (2025). Recombinant DNA technology. NHGRI.
- Mitra, M. S., et al. (2020). Development of peptide therapeutics: A nonclinical safety assessment perspective. Regulatory Toxicology and Pharmacology, 117, 104766.
- U.S. Food & Drug Administration. (2024). Immunogenicity of protein-based therapeutics. FDA.
- Smith, C. M., et al. (2011). Novel immunogenic peptides elicit systemic anaphylaxis in mice: Implications for peptide vaccines. Journal of Immunology, 187(3), 1201-1206.
- Cianfarani, S. (2019). Risk of cancer in patients treated with recombinant human growth hormone in childhood. Annals of Pediatric Endocrinology & Metabolism, 24(2), 92-98.
- U.S. Food & Drug Administration. (2024). Certain bulk drug substances for use in compounding that may present significant safety risks. FDA.
- U.S. Food & Drug Administration, et al. (2016). Pharmacy compounding of human drug products under Section 503A of the Federal Food, Drug, and Cosmetic Act: Guidance. FDA.
- National Academies of Sciences, Engineering, and Medicine, et al. (2020). The clinical utility of compounded bioidentical hormone therapy: A review of safety, effectiveness, and use: Regulatory framework for compounded preparations. National Academies Press.
- U.S. Food & Drug Administration. (2024). Bulk drug substances nominated for use in compounding under Section 503A of the Federal Food, Drug, and Cosmetic Act. FDA.
- U.S. Food & Drug Administration. (2016). Prescription requirement under Section 503A of the Federal Food, Drug, and Cosmetic Act; Draft guidance for industry; Availability. FDA.
- Goles, M., et al. (2024). Peptide-based drug discovery through artificial intelligence: Towards an autonomous design of therapeutic peptides. Briefings in Bioinformatics, 25(4).
- Kulkarni, S. (2025). Prime time for peptide-based drug discovery. Drug Discovery & Development.
- Müller, T., et al. (2019). Glucagon-like peptide 1 (GLP-1). Molecular Metabolism, 30, 72-130.
- Mackie, A. R., et al. (2013). Specific food structures suppress appetite through reduced gastric emptying rate. American Journal of Physiology - Gastrointestinal and Liver Physiology, 304(11), G1038-G1043.
- Goyal, R. K., Cristofaro, V., & Sullivan, M. P. (2019). Rapid gastric emptying in diabetes mellitus: Pathophysiology and clinical importance. Journal of Diabetes and its Complications, 33(11), 107414.
- Chiu, C. J., Wray, L. A., & Beverly, E. A. (2010). Relationship of glucose regulation to changes in weight: a systematic review and guide to future research. Diabetes/Metabolism Research and Reviews, 26(5), 323-335.
- Frías, J. P., et al. (2021). Tirzepatide versus semaglutide once weekly in patients with type 2 diabetes. The New England Journal of Medicine, 385(6), 503-515.
- Cleveland Clinic. (2022). Human growth hormone (HGH). Cleveland Clinic.
- Kubo, H., et al. (2022). Insulin-like growth factor-1 levels are associated with high comorbidity of metabolic disorders in obese subjects; a Japanese single-center, retrospective study. Scientific Reports, 12(1), 1-9.
- Lee, C., et al. (2015). The mitochondrial-derived peptide MOTS-c promotes metabolic homeostasis and reduces obesity and insulin resistance. Cell Metabolism, 21(3), 443-454.
- Zhe, W., et al. (2024). Central and peripheral mechanism of MOTS-c attenuates pain hypersensitivity in a mice model of inflammatory pain. Neurological Research, 46(2), 165-177.
- Yi, X., et al. (2023). Role of MOTS-c in the regulation of bone metabolism. Frontiers in Physiology, 14, 1149120.
- Hamazaki, J., & Murata, S. (2024). Relationships between protein degradation, cellular senescence, and organismal aging. The Journal of Biochemistry, 175(5), 473-480.
- Johns Hopkins Medicine. (2019). Immune cells age and die prematurely in people with very short telomeres, according to new study. Johns Hopkins Medicine.
- Mayo Clinic Staff. (2023). Melatonin. Mayo Clinic.
- Pollard, B. J., & Pomfrett, C. J. D. (2001). Delta sleep-inducing peptide. European Journal of Anaesthesiology, 18(7), 419-422.
- Dominari, A., et al. (2020). Thymosin alpha 1: A comprehensive review of the literature. World Journal of Virology, 9(5), 67-78.
- Pickart, L., & Margolina, A. (2018). Regenerative and protective actions of the GHK-Cu peptide in the light of the new gene data. International Journal of Molecular Sciences, 19(7), 1987.
- Mayo Clinic Staff. (2023). Diabetes treatment: Using insulin to manage blood sugar. Mayo Clinic.
- Koroleva, S. V., & Mjasoedov, N. F. (2019). Physiological effects of Selank and its fragments. Biology Bulletin of the Russian Academy of Sciences, 46, 407-414.
- Bathina, S., & Das, U. N. (2015). Brain-derived neurotrophic factor and its clinical implications. Archives of Medical Science, 11(6), 1164-1178.
- Karantysh, G. V., et al. (2020). Effect of Pinealon on learning and expression of NMDA receptor subunit genes in the hippocampus of rats with experimental diabetes. Neurochemical Journal, 14, 314-320.
- Edinoff, A. N., et al. (2022). Bremelanotide for treatment of female hypoactive sexual desire. Neurology International, 14(1), 75-88.
- Pachano Pesantez, G. S., & Clayton, A. H. (2021). Treatment of hypoactive sexual desire disorder among women: General considerations and pharmacological options. Focus, 19(1), 39-45.
- Kingsberg, S. A., et al. (2019). Bremelanotide for the treatment of hypoactive sexual desire disorder: Two randomized phase 3 trials. Obstetrics and Gynecology, 134(5), 899-908.
- Diamond, L., et al. (2005). Co-administration of low doses of intranasal PT-141, a melanocortin receptor agonist, and sildenafil to men with erectile dysfunction results in an enhanced erectile response. Urology, 65(4), 755-759.
- Gao, S., et al. (2016). Oxytocin, the peptide that bonds the sexes also divides them. Proceedings of the National Academy of Sciences, 113(27), 7650-7654.
- Melis, M. R., & Argiolas, A. (2021). Oxytocin, erectile function and sexual behavior: last discoveries and possible advances. International Journal of Molecular Sciences, 22(19), 10376.

Copyright © Innerbody Research 1997 - 2025. All Rights Reserved.
